Home
» Tumor
»
Why a Benign Growth May Still Need Follow-Up Imaging
Why a Benign Growth May Still Need Follow-Up Imaging
“Benign” sounds final, but a follow-up scan can still be part of a careful plan. In some cases, the radiologist means that a finding looks likely to be harmless on the current images, not that a tissue sample has proved exactly what it is. In other cases, a growth is known to be noncancerous, yet its location, size, symptoms, or tendency to recur may make monitoring useful. The reason depends on the specific finding; a follow-up recommendation does not, by itself, mean that cancer is suspected.
In 2026, the American College of Radiology’s BI-RADS v2025 manual provides updated standardized breast-imaging terms and management recommendations. For patients, a practical example is BI-RADS 3: “probably benign” findings may be followed with short-term imaging to check for stability. That category is different from a finding described as definitively benign. The same logic—clarify what is known, what remains uncertain, and what change would matter—helps with other incidental growths too.
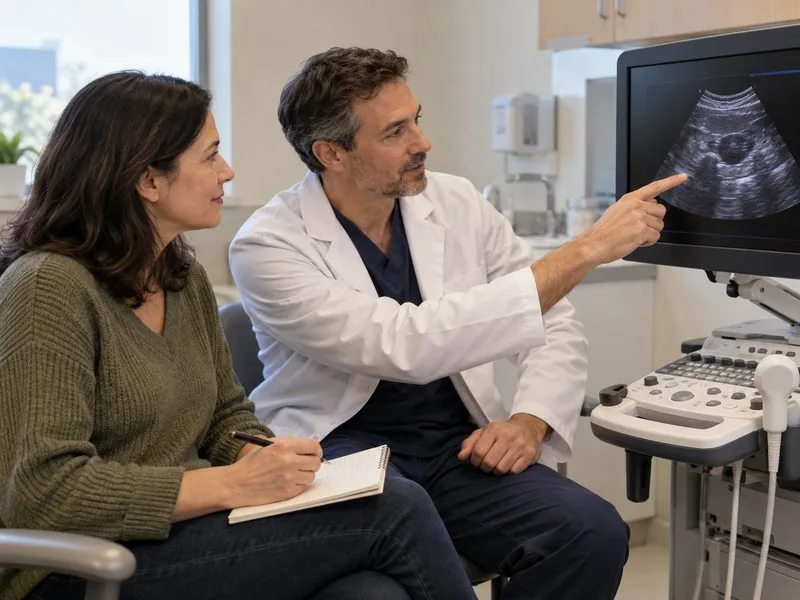
A radiologist reviews an ultrasound image with a patient, who writes down questions about the finding and recommended follow-up.
What does “benign” mean, and how certain is the report?
The National Cancer Institute defines a benign tumor as a growth that is not cancer and does not invade nearby tissue or spread to other parts of the body. But reports do not always use “benign” to mean the same level of certainty. A pathologist may identify a growth as benign after examining tissue. An imaging report may instead say “benign-appearing,” “likely benign,” or “probably benign,” based on how it looks on a scan. Those descriptions are reassuring, but they are not identical to a tissue diagnosis.
Ask your clinician which description applies to your result. Useful questions include:
Is this confirmed benign, or does it only look probably benign on imaging?
What specific features make it appear benign?
Did the scan answer the original clinical question, or is any part still uncertain?
Would reviewing an older scan, using a different imaging method, or taking a tissue sample change the level of certainty?
These distinctions matter because the next step should match the actual degree of certainty and the person’s health context. A short-interval scan may be a way to gather evidence over time, while other findings may need no extra imaging or may call for a different evaluation.
Why monitor something that appears harmless?
Follow-up imaging can answer a question that a single snapshot cannot: does the finding stay the same? It can also help clarify its shape or composition, compare it with earlier images, or show whether it is affecting nearby structures. These are reasons for monitoring, not predictions that a growth will become cancer.
To confirm stability: A scan at a planned interval gives clinicians a comparison point. No meaningful change may support the original low-concern interpretation, although the meaning of stability depends on the type of growth and the recommended surveillance plan.
To complete characterization: The first exam may not show enough detail. The radiologist may suggest another view, ultrasound, MRI, CT, or a contrast-enhanced study to answer a specific question.
To account for location or function: A noncancerous mass can still matter if it presses on a nerve or organ, affects movement, causes symptoms, or changes how an organ works. The relevant concern varies by body part.
To watch for recurrence or change after treatment: Some known benign growths can return or change after removal or other treatment. The care team may recommend surveillance based on the growth’s type and history.
To apply a condition-specific guideline: Age, symptoms, medical history, risk factors, and the appearance and size of a lesion can affect whether follow-up is useful. ACR guidance for incidental findings is designed for defined patient groups and also recognizes the risk of unnecessary testing when a finding is very low risk.
For example, the ACR and RadiologyInfo explain that a breast-imaging finding labeled BI-RADS 3 is probably benign and typically receives short-term follow-up imaging to check that it does not grow or change. BI-RADS categories 1 and 2, in contrast, describe negative or benign findings that generally do not need additional follow-up beyond routine screening. These breast-specific categories should not be applied to a growth found elsewhere in the body.
Does a follow-up scan mean the growth is becoming cancer?
No. Follow-up is often recommended precisely because the available evidence is reassuring but not complete, or because a change over time would help confirm the interpretation. “Probably benign” is a probability-based imaging assessment; it is not the same as a diagnosis of cancer, and a recommendation to recheck does not mean a clinician expects the finding to worsen.
At the same time, a benign-looking report should not be used to ignore a new symptom or skip the recommended check. Imaging has limits, and its meaning depends on the reason for the exam and the clinical examination. The ACR notes that some new breast lumps need continued clinical follow-up even when initial imaging is normal. That example illustrates why a scan result and a person’s symptoms must be considered together.
Which parts of the report should you check first?
Start with the “Impression” or “Conclusion,” then read the “Recommendation” section. These usually state the radiologist’s main assessment and what, if anything, should happen next. Look for the exact wording: “benign,” “probably benign,” “indeterminate,” “stable,” “increased in size,” “additional imaging,” “biopsy,” or a specific follow-up interval. Do not treat one word as a complete interpretation; ask the ordering clinician to explain it in context.
Check whether the report mentions comparison with prior images. A previous scan from another clinic may not have been available to the radiologist. If you have older images or reports, ask whether they should be sent to the imaging center. Comparison can show that a finding is unchanged or that it is new, and may affect the recommendation.
What should you ask before scheduling the next scan?
Write down the recommendation and clarify the plan before leaving the appointment or ending the call. You can ask:
What is the purpose of this follow-up: confirm stability, get a clearer view, or look for a specific change?
How soon should it happen, and what is the reason for that interval?
Which imaging test is recommended, and will it use radiation, contrast, or a different technique?
Who will place the order, schedule the test, and tell me the result?
What could change the plan—for example, a size change, a new symptom, or a different comparison scan?
What symptoms should prompt me to call sooner?
There is no single follow-up schedule for every “benign growth.” The appropriate interval can differ by body part, type of finding, age, symptoms, risk factors, and prior imaging. Do not substitute a general online schedule for the interval written in your report or recommended by your clinician.
When should you contact the clinician promptly?
Contact the ordering clinician promptly if the report says “suspicious,” “indeterminate,” “interval growth,” recommends biopsy or urgent evaluation, or gives a firm deadline that is approaching. Ask the care team how quickly the recommendation should be carried out and who is responsible for arranging it. A finding that has changed does not automatically mean cancer, but it does deserve the specific review recommended by the radiologist.
Seek medical advice sooner if you develop a new or worsening symptom related to the area, such as increasing pain, weakness, numbness, difficulty swallowing, or a noticeable change in function. The relevant warning signs depend on where the growth is, so ask the clinician for guidance specific to your report. Severe or rapidly worsening symptoms should be assessed urgently rather than waiting for a routine scan.
If the report seems to say “benign” but also recommends follow-up, ask the clinician to reconcile those statements. Often the recommendation simply means, “This looks low risk; let’s make sure it stays that way.” The useful outcome is a clear explanation of what is known, what the next scan is meant to establish, and how you will receive the result.